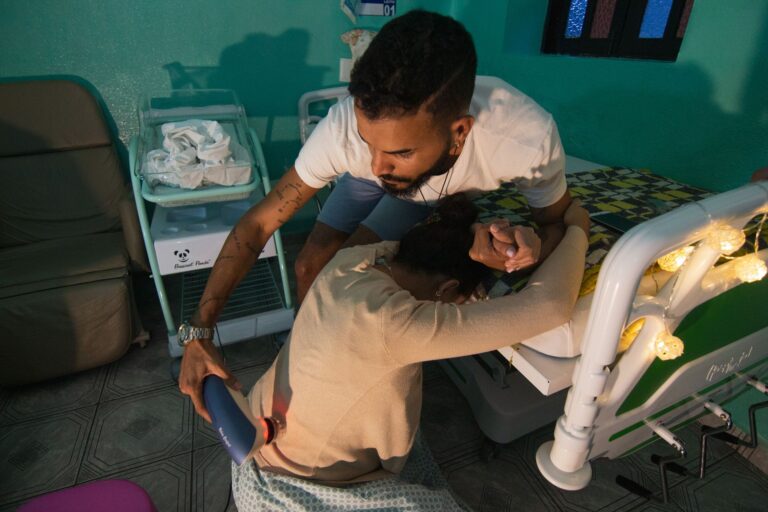
Prenatal care for LGBTQ+ pregnant partners follows the same medical pathway as care for any other pregnant person: regular appointments to monitor fetal development, maternal health, and pregnancy complications, plus screening for genetic conditions and infections. What changes is how you navigate the healthcare system itself—finding providers who recognize your identity, understand your medical history, and deliver care without assumptions about gender, sexuality, or family structure.
Whether you are a transgender man, a non-binary person, or a cisgender partner in an LGBTQ+ relationship, the physical exams, blood tests, and ultrasounds remain identical. The difference lies in building a team that listens, asks before assuming, and treats your pregnancy as legitimate regardless of how you identify. This article walks through what standard prenatal care includes, how to find affirming providers, what medical conversations matter most, and what to do if you encounter barriers.
Table of Contents
- What Prenatal Care Visits Include
- Choosing a Provider and Finding Affirming Care
- Medical History and Testosterone Use
- Prenatal Screening, Testing, and Informed Choice
- Managing Chronic Conditions and Mental Health
- Legal Documentation and Parental Rights
- What to Tell Your Provider About Your Relationship and Family
- Navigating Discrimination and Speaking Up
- Preparing for Labor, Delivery, and the Hospital
- Building Your Long-Term Support System
- Frequently Asked Questions
What Prenatal Care Visits Include
Prenatal care starts with an initial appointment, often called the first trimester visit, that typically occurs between eight and twelve weeks of pregnancy. Your provider will take a full medical and reproductive history, confirm the pregnancy with a blood test or ultrasound, establish your due date, and check your baseline blood pressure and weight.
This first visit is long—often one to two hours—because it sets the foundation for all future care. Routine visits after that occur roughly once monthly through week 28, every two weeks from 28 to 36 weeks, then weekly until delivery. At each visit, you have your blood pressure checked, your urine tested for protein and glucose, and your abdomen measured to track fetal growth.
Your provider will listen to the fetal heartbeat with a handheld Doppler (a small ultrasound device) starting around 10 weeks. Specific screening and testing happens at set points. Around 11 to 14 weeks, many providers offer a first-trimester screening that combines an ultrasound measurement (nuchal translucency) with blood tests to estimate risk for conditions like Down syndrome.
Around 15 to 22 weeks, a second-trimester screening offers similar estimates. An anatomy scan ultrasound between 18 and 22 weeks checks the baby's organs, brain, heart, and limbs for major structural concerns. Screening for gestational diabetes occurs around 24 to 28 weeks using a glucose tolerance test. A test for anemia happens in the first and third trimesters.
Screening for group B streptococcus (GBS)—a bacteria harmless to you but risky for newborns during delivery—occurs around 35 to 37 weeks and involves a quick swab of your vagina and rectum. Blood tests early in pregnancy also screen for syphilis, HIV, hepatitis B and C, and immunity to rubella. If you have a chronic condition like diabetes, high blood pressure, or a history of miscarriage, your care may involve more frequent visits, specialty referrals, or monitoring that extends beyond these standard benchmarks.
Choosing a Provider and Finding Affirming Care
Finding a provider who actively affirms LGBTQ+ identity is not a luxury—it directly affects communication, the accuracy of your medical history, and whether you feel safe being honest about your circumstances. Start by calling clinics directly and asking: "Do you have experience caring for transgender and non-binary pregnant people?" or "How do you document gender identity in your records?" Honest, practiced answers suggest they have thought through these questions.
Look for providers and clinics that explicitly list LGBTQ+ inclusion in their website mission or patient resources. Local LGBTQ+ health centers or community health centers often have obstetric services or referral networks. The American College of Obstetricians and Gynecologists (ACOG) and the National LGBTQ+ Health Education Center both publish directories and guidance that can help you locate affirming practices in your area.
Ask specifically about documentation: How will they refer to you in charts? Will they use your chosen name if it differs from legal documents? Will they accurately record your gender identity separately from your sex assigned at birth—a distinction that matters because your reproductive anatomy is what requires prenatal care, not your gender? Some offices use templates that ask whether you are pregnant, whereas others assume all pregnant patients are women and require you to correct them repeatedly. When you call, notice whether the staff member answering seems comfortable with your questions or defensive.
Notice whether they ask for clarification or make you repeat yourself. A good fit will ask what pronouns you use and remember them. They will not assume your relationship to a partner or require you to bring one to appointments. If you have had previous poor experiences with healthcare, acknowledge that going in: "I have had a negative experience with a provider before.
I need to know you are open to feedback if something does not feel right." Providers worth keeping will take that seriously and check in with you about how you are feeling in the relationship. If you cannot find an explicitly LGBTQ+ friendly provider in your area, you can still prepare yourself to receive good care.
Write down your key medical history and identity information before your first appointment. Correct assumptions gently but firmly: "I use they/them pronouns" or "I am transgender and I need my records to reflect that." Document what the provider says in case you need to follow up later.
Medical History and Testosterone Use
If you have ever taken hormone therapy—testosterone, estrogen blockers, or other medications—tell your provider at your first visit, including how long you took it, how recently you stopped, and what form it was (injection, gel, pill, patch). This is not about judgment; it is about medical accuracy. Your provider needs to know what has been in your body to interpret your current health status and anticipate what might develop.
Testosterone use does not damage fertility or harm a fetus, and you do not need to stop it before becoming pregnant—but you will likely stop it during pregnancy because testosterone crosses the placenta and can affect fetal development. If you have been on testosterone, your uterus and fallopian tubes are unchanged and functional, even if you have had a hysterectomy (which is not reversible, but partial uterine surgeries or non-surgical sterilization can sometimes be reversed).
Some people on testosterone have lighter periods or no periods at all, which can make it harder to know when pregnancy begins. If you are trying to become pregnant, talk with your provider about how to track ovulation or determine pregnancy timing. A home pregnancy test (urine or blood) will show a positive result before you would detect other signs of pregnancy.
Your provider will also ask about any chest surgery you may have had. If you have had a double mastectomy or breast tissue removal, this does not prevent breastfeeding, though it may affect your ability to produce enough milk on your own. This is important information to share early so your care team can connect you with lactation support if you want to breastfeed.
If you have had any reproductive surgeries—hysterectomy, removal of ovaries, tubal ligation, or placement of an IUD or implant—these details matter for understanding your fertility status and your current anatomy. Be specific: a provider needs to know which organs you have and which ones you do not.
Prenatal Screening, Testing, and Informed Choice
Prenatal screening and testing can feel overwhelming because there are multiple options at different pregnancy stages, and each one carries small risks alongside potential information. Your provider should explain each option—what it measures, how accurate it is, what the results mean, what you would do with the information, and what discomfort or risk it involves.
You have the right to decline any test. Some tests are screening: they estimate risk but do not tell you definitively whether a condition is present. The first-trimester and second-trimester screening tests (which combine ultrasound and blood work) are screening tests. If the results suggest elevated risk, your provider will typically offer a diagnostic test like amniocentesis or non-invasive prenatal testing (NIPT, also called cell-free fetal DNA testing) if you want more certainty.
NIPT analyzes fetal DNA fragments in your blood and can be done from 10 weeks onward. It has very high accuracy (around 99%) for detecting Down syndrome and is lower-risk than amniocentesis because it requires only a blood draw, not a procedure that enters the uterus. It is also more expensive and not always covered by insurance.
Amniocentesis involves inserting a needle through the abdomen into the amniotic sac to collect fluid; it carries a small risk of miscarriage (often quoted as less than 1 in 400) but provides definitive genetic information. The anatomy scan ultrasound at 18 to 22 weeks is standard and will check the baby's heart, brain, spine, kidneys, and limbs.
If the provider finds something unusual, they may recommend a targeted ultrasound with a specialist or a different imaging test like fetal MRI. These referrals can feel scary but are intended to give you and your medical team clearer information before delivery. Some tests screen for infectious diseases: syphilis, HIV, hepatitis. These are standard and important.
If results come back positive, your provider has treatment options that reduce or eliminate the risk of transmission to your baby. Do not avoid testing because you are afraid of a positive result; knowing your status is how you protect your baby and yourself. Carrier screening for genetic conditions (like sickle cell, cystic fibrosis, or thalassemia) is optional and may be offered based on your ancestry or ethnicity. This is worth discussing with your provider if you have a family history of genetic disease or if you are using donor sperm or eggs from someone whose background includes certain conditions.
Managing Chronic Conditions and Mental Health
If you have a chronic condition—diabetes, high blood pressure, asthma, lupus, or any other long-term illness—you need prenatal care that coordinates with your existing care team. Ideally, your obstetrician and your other specialists (endocrinologist, rheumatologist, cardiologist) communicate regularly. This means sharing records and aligning medication plans so that your pregnancy is managed as a whole, not as separate problems.
Some medications are safe during pregnancy; others are not. Do not stop taking a medication on your own because you are worried about your pregnancy—stopping suddenly can be more dangerous than the medication itself. Instead, talk with your prescribing provider and your obstetrician together about whether to continue, switch, or adjust doses. This conversation is most important for medications treating conditions that matter to your health: blood pressure medication, asthma inhalers, psychiatric medications, and medications for conditions like lupus or diabetes.
Mental health during pregnancy and postpartum is a significant part of your care. Tell your provider if you have a history of depression, anxiety, bipolar disorder, or post-traumatic stress. Pregnancy can trigger or worsen these conditions, and untreated mental illness poses real risks to both you and your baby. Many psychiatric medications are safe during pregnancy.
If you are not on medication but you think you should be, ask for a referral to a mental health provider who has experience with pregnant people. LGBTQ+ individuals face specific stressors during pregnancy: discrimination from healthcare providers, social isolation if you are not out, uncertainty about your legal status as a parent, or worry about how others will react to your pregnancy.
These are real stressors, not something to minimize, and they deserve support. Ask whether your clinic has a therapist or social worker on staff who understands LGBTQ+ health. If not, look for one independently.
Legal Documentation and Parental Rights
Legal parentage after delivery depends on who gave birth, what state you live in, and whether there is a partnership agreement. The person who gives birth is the legal parent in every state. A spouse or partner may not be automatically listed on the birth certificate, depending on how you married and what state you live in.
This is urgent to clarify before delivery. If you are married to your partner, your state should recognize your partner as a legal parent of a baby born during the marriage, but the specifics vary. In some states, this is automatic. In others, you need to file additional paperwork or have your partner formally adopt the child.
Some states have changed these rules recently; your local family law attorney or LGBTQ+ legal services organization can tell you what applies where you are. If you are not married, your partner is not a legal parent unless they adopt your child or you have put adoption paperwork in place. An adoption after birth is straightforward in most places and is worth doing to clarify legal rights around custody, inheritance, healthcare decisions, and guardianship if something happens to you.
Adoption also makes a second parent's relationship to the child clear on the birth certificate in many states. Before you deliver, complete any legal paperwork your attorney recommends: a birth plan that names your partner as the person who makes medical decisions if you are unable to, a will that names guardians for your child, and adoption documents if you are not married.
Have these in place before labor so that there is no ambiguity about what you want. Your birth certificate and all parenting documents should reflect your legal name, not your chosen name, unless you have legally changed your name. If you want your birth certificate to list a chosen name, you have the option to legally change your name before or after delivery in most states.
What to Tell Your Provider About Your Relationship and Family
At your first appointment, you will be asked whether you are in a relationship and about your living situation. You do not have to answer any question that feels unsafe, but providing accurate information helps your provider understand your support system and whether you have resources to manage a pregnancy and a newborn. Be honest about whether you have a partner, how long you have been together, whether your partner will be involved in parenting, and whether your relationship is stable.
If you are not certain about what your partner's role will be, say that. If your partner is unsupportive or abusive, tell your provider or the clinic social worker. Pregnancy abuse is common, and your healthcare team can connect you with resources. If you are parenting with multiple people—a spouse, an ex, a close friend—or if you are sharing parenting in an unconventional arrangement, tell your provider how you want to be supported.
Your medical team does not have to understand alternative family structures, but they need to know who is present in your life and who you want at your appointments. Some LGBTQ+ people are estranged from biological family and have built chosen family—close friends who function as kin. These people matter in your care story. Tell your provider if there is a chosen family member you want making healthcare decisions for you or being present at delivery, and bring that person's contact information.
If you are a same-sex couple and one of you is pregnant, the non-pregnant partner may be questioned about your relationship or told they cannot be present at appointments or delivery. This is not medically justified and violates most healthcare settings' non-discrimination policies. If it happens, tell clinic leadership immediately. You can also write a birth plan that clearly states who you want present and what role they play.
Navigating Discrimination and Speaking Up
Some healthcare providers hold biases against LGBTQ+ people, whether conscious or not. You might encounter a provider who repeatedly uses the wrong pronouns, refuses to document your gender identity, makes assumptions about your sexuality, or suggests you are making a mistake by having a baby. These are red flags, and you should not accept them.
If a provider misgenders you once, you can gently correct them: "I use they/them pronouns." If they do it repeatedly or refuse to use your pronouns after you have corrected them, that is unprofessional and you can escalate it to the clinic manager or find a different provider. You should not have to spend your pregnancy correcting a provider about basic respect.
If a provider suggests your pregnancy is dangerous or inadvisable because of your gender identity or sexual orientation, ask them to explain their medical concern. Gender identity is not a medical risk factor for pregnancy. Sexual orientation is not a medical risk factor. Discrimination is not medicine. If you experience discrimination, you can file a complaint with your state's medical board, the clinic administrator, or your insurance company.
LGBTQ+ legal services organizations can help you navigate these complaints. You can also leave before a visit if you feel unsafe or disrespected, even if you have to reschedule. Finding another provider takes time, especially if you live somewhere with limited options. You can ask whether your clinic has multiple OB providers and whether you can switch, or you can call other clinics to see if they have openings.
Some people travel to a larger city for prenatal care if their local options are not affirming. This is not ideal, but it is sometimes necessary.
Preparing for Labor, Delivery, and the Hospital
Before you deliver, prepare a birth plan that identifies you, states your pronouns and what name you want used, and explains what you want during labor and delivery. Write clearly: "Please use they/them pronouns" or "I use my legal name, but my preferred name is ___." Hand a copy to every person on your care team and bring extra copies to the hospital.
Tell your birth team early whether you want to breastfeed, bottle-feed, or both. If you are transgender and worried about how your chest is perceived during skin-to-skin contact with your baby or during hospital gowning, tell your nurse or provider. You can wear your own shirt or request one that works better for you. You can ask for privacy during exams.
You can request a private room if possible. These are reasonable requests and most hospitals will accommodate them. If you are admitted to a labor-and-delivery floor, the staff will review your chart and should see your recorded gender identity. If they still misgender you, correct them directly: "I go by they/them." You can also ask your partner to speak up if you are in active labor.
Most hospital staff are responsive if you state your needs clearly. After delivery, your baby will go to a nursery or stay in your room depending on the hospital. You will have a hospital gown, a catheter if you have an epidural, possible bleeding, and possibly difficulty walking or sitting. Tell the staff what kind of support you need.
Ask for a private room or a bed near a curtain if you are worried about your body being visible. Ask for frequent checks on your pain level. Tell them if you are uncomfortable. Postpartum depression, anxiety, and psychosis can affect anyone. If you have a history of mental illness, tell your provider before delivery and ask about monitoring in the early weeks after delivery.
Hormonal changes after birth can trigger or worsen mood disorders. You deserve support, not judgment.
Building Your Long-Term Support System
After delivery, you will have a six-week postpartum visit with your obstetrician to check your physical healing. This is the right time to ask about resuming exercise, returning to work, and managing any ongoing concerns. If you had any complications during pregnancy or delivery, this visit is important for understanding what happened and what it means for future pregnancies.
You will also need a pediatrician for your baby. This is a good opportunity to work with a provider who is explicitly LGBTQ+ affirming and who is prepared to support a family with LGBTQ+ parents. Many pediatricians have explicit language about LGBTQ+ inclusion on their website or in their intake forms. You can call and ask: "How do you handle situations where a baby has two mothers, two fathers, or a non-binary parent?" If you plan to breastfeed, you will likely benefit from lactation support.
Lactation consultants can help with positioning, latch, supply, and any painful or difficult situations. Some insurance plans cover a few visits; some hospitals provide referrals. If you have had chest surgery or are taking medication that might affect milk production, lactation support is especially valuable. Postpartum is when you most need your support network—partner, family, chosen family, friends, or community.
Make a plan before delivery for who will help during the first weeks, whether for cooking, cleaning, childcare for other children, or just sitting with you. If you do not have reliable support, ask your clinic social worker about postpartum doulas, community support programs, or faith organizations that provide practical help regardless of sexual orientation or gender identity.
Your mental health matters in the postpartum period. If you have a therapist, schedule a visit for shortly after delivery. If you do not, this is the time to start. Postpartum depression and anxiety are treatable and common, and they are not a reflection of how much you love your baby or whether you will be a good parent.
Frequently Asked Questions
Does being transgender or non-binary affect what prenatal care I need?
No. The medical care is identical to any pregnancy: regular appointments, screening tests, and monitoring. What changes is finding providers who recognize your identity, ask before assuming your pronouns or family structure, and document your gender identity accurately in your records.
What should I tell my provider about hormone therapy I took before pregnancy?
Tell your provider what type of hormone therapy you took, how long you took it, and when you stopped. Testosterone does not harm a pregnancy or a fetus, but you will likely stop it during pregnancy because testosterone crosses the placenta. Your provider needs this history to interpret your current health accurately.
Will my partner be recognized as a legal parent after delivery?
That depends on your state and whether you are married. If you are married, your spouse should be a legal parent, but the automatic rules vary by state. If you are not married, your partner is not a legal parent unless they adopt your child. Speak with a family law attorney before delivery to clarify what paperwork you need where you live.
What do I do if my healthcare provider misgenders me or is disrespectful?
Correct them gently the first time: "I use they/them pronouns." If they repeat the mistake or refuse to respect your identity after correction, that is unprofessional. You can switch providers, file a complaint with the clinic or your state medical board, or escalate to the clinic manager. You should not have to spend your pregnancy correcting a provider about basic respect.
Is there a higher medical risk to pregnancy because I am LGBTQ+?
No. Gender identity and sexual orientation are not medical risk factors for pregnancy. Medical risk comes from factors like age, chronic illness, previous pregnancy complications, or smoking—the same factors that affect anyone. If a provider suggests otherwise, they are discriminating, not practicing medicine.
What should I include in my birth plan for the hospital?
Include your pronouns, what name you want used, who you want present, and any requests about privacy or your comfort during labor and delivery. Give a copy to your birth team in advance. If you are worried about your body being visible or about how your chest is perceived during skin-to-skin contact, say that clearly. Most hospitals will accommodate these requests.